
COURSE · PART 2 · MODULE 7 · PAGE 3
Salience, Arousal, and Feedback Loops
Lesson 20 explores salience, arousal, and feedback loops through everyday examples, collaborative adaptations and clinical reasoning.
The Person section was human-authored and approved October 30, 2026; the Clinician section and Supporter section were human-edited and approved November 3, 2026. Audit 1 corrections were accepted and applied November 4, 2026.
For the Person With FND
For Family, Friends, and Other Supporters
For Clinicians and the Care Team
Research and Sources
For the Person With FND
How did you hear your name?
Imagine you’re sitting in a busy café.
People are talking. Dishes are clattering. Somewhere behind you, a coffee machine is steaming milk.
You’re listening to someone at your table when you hear your name spoken across the room.
Suddenly, that voice stands out.
It wasn’t necessarily louder than everything else. And you weren’t deliberately listening for it.
Yet your brain recognized something important.
You turn your head to see who called you.
Why did your name stand out when so many other sounds didn’t?
The answer introduces our first new term.
Salience: The importance your brain gives to information, helping decide what deserves attention.
Your name was important to you, so your brain gave it priority.
But importance doesn’t always mean something is dangerous.
A familiar voice, a delicious smell or a favourite song can all stand out.
So can pain, a sudden noise or an unexpected movement.
Salience helps your brain decide what deserves attention among all the information arriving from your senses.
Your brain can’t give everything equal attention
Think back to Lesson 19.
We learned that our sensory systems provide information from the world, our body position and inside our body.
But imagine trying to pay equal attention to every sound, sensation and movement all at once.
It would be exhausting!
Fortunately, your nervous system doesn’t treat every piece of information as equally important.
You’re reading a book.
The chair supports your back. Your clothing touches your skin. There’s a faint humming sound in the room.
Most of those sensations aren’t demanding much attention.
Then your phone rings.
Your attention shifts toward the sound.
Or perhaps you suddenly feel a sharp pain in your foot.
Now that sensation becomes important.
Your brain is constantly deciding which information needs attention and which can remain in the background. [1]
But what happens when several things compete to be important at the same time?
When everything seems important
Return to our café.
You’re having a pleasant conversation.
Then someone starts grinding coffee beans.
A child cries nearby.
Your chair has become uncomfortable, and the headache you’ve had all morning feels more noticeable.
You try to follow the conversation, but your attention keeps shifting.
The coffee grinder stops.
For a moment, you can listen more easily.
Then someone drops a metal tray.
You lose track of what your friend was saying.
Nothing about the conversation itself has become more complicated.
But more of the information around you is competing for your attention.
And when your nervous system has difficulty deciding what to prioritize, an ordinary activity can become much harder.
For someone living with FND, migraine, sensory sensitivity or other conditions, this situation may be particularly demanding.
That’s one reason understanding salience can be helpful.
But there’s another part of the story.
Your body’s level of readiness
Imagine you’re resting in a comfortable chair.
Your breathing is easy. Your muscles aren’t preparing for much activity.
Then a loud crash comes from the kitchen!
You may sit upright, turn toward the sound or feel your heart beating faster.
Your nervous system has shifted into a more alert state.
Scientists have a name for this.
Arousal: Your nervous system’s level of alertness and readiness to respond. It can change with activity, excitement, pain, illness, surprise and many other experiences.
Arousal isn’t necessarily fear or anxiety.
Think about riding a bicycle on a beautiful morning.
You feel energetic and alert. Your body is ready to respond to the road ahead.
Or imagine becoming excited while watching your favourite team play.
Your arousal may increase, even though you’re enjoying yourself.
Now think about being exhausted after a long day.
You might feel less alert and have difficulty concentrating.
These changes are part of ordinary life.
Your nervous system adjusts its readiness depending on what you’re doing and what’s happening around you.
And this brings us to an important distinction:
Salience concerns what receives priority. Arousal concerns how ready your nervous system is to respond.
They can affect each other, but they aren’t the same thing.
When one change affects another
Let’s return to the café one last time.
You have a headache and are trying to follow a conversation.
The grinder starts again.
You find yourself concentrating harder to hear your friend.
That extra effort makes you tired.
As you become more tired, following the conversation gets harder.
Now you need even more effort to keep up.
Notice what’s happening.
Difficulty following the conversation leads to more effort.
More effort contributes to tiredness.
Tiredness makes following the conversation harder.
Each change can influence the next.
Feedback loop: When two or more things affect one another over time, creating a cycle that may increase, reduce or maintain what is happening.
We can imagine the cycle like this:
Difficulty following a conversation → More effort → Greater tiredness → More difficulty following the conversation.
You’ve probably experienced something similar, even without FND.
Perhaps pain makes it difficult to sleep, and poor sleep makes the pain harder to manage the next day.
Or worrying about being late makes you rush, and rushing causes mistakes that delay you further.
These examples help us understand how one difficulty can influence another.
A feedback loop isn’t necessarily the original cause of the problem.
It describes how several things may continue affecting one another.
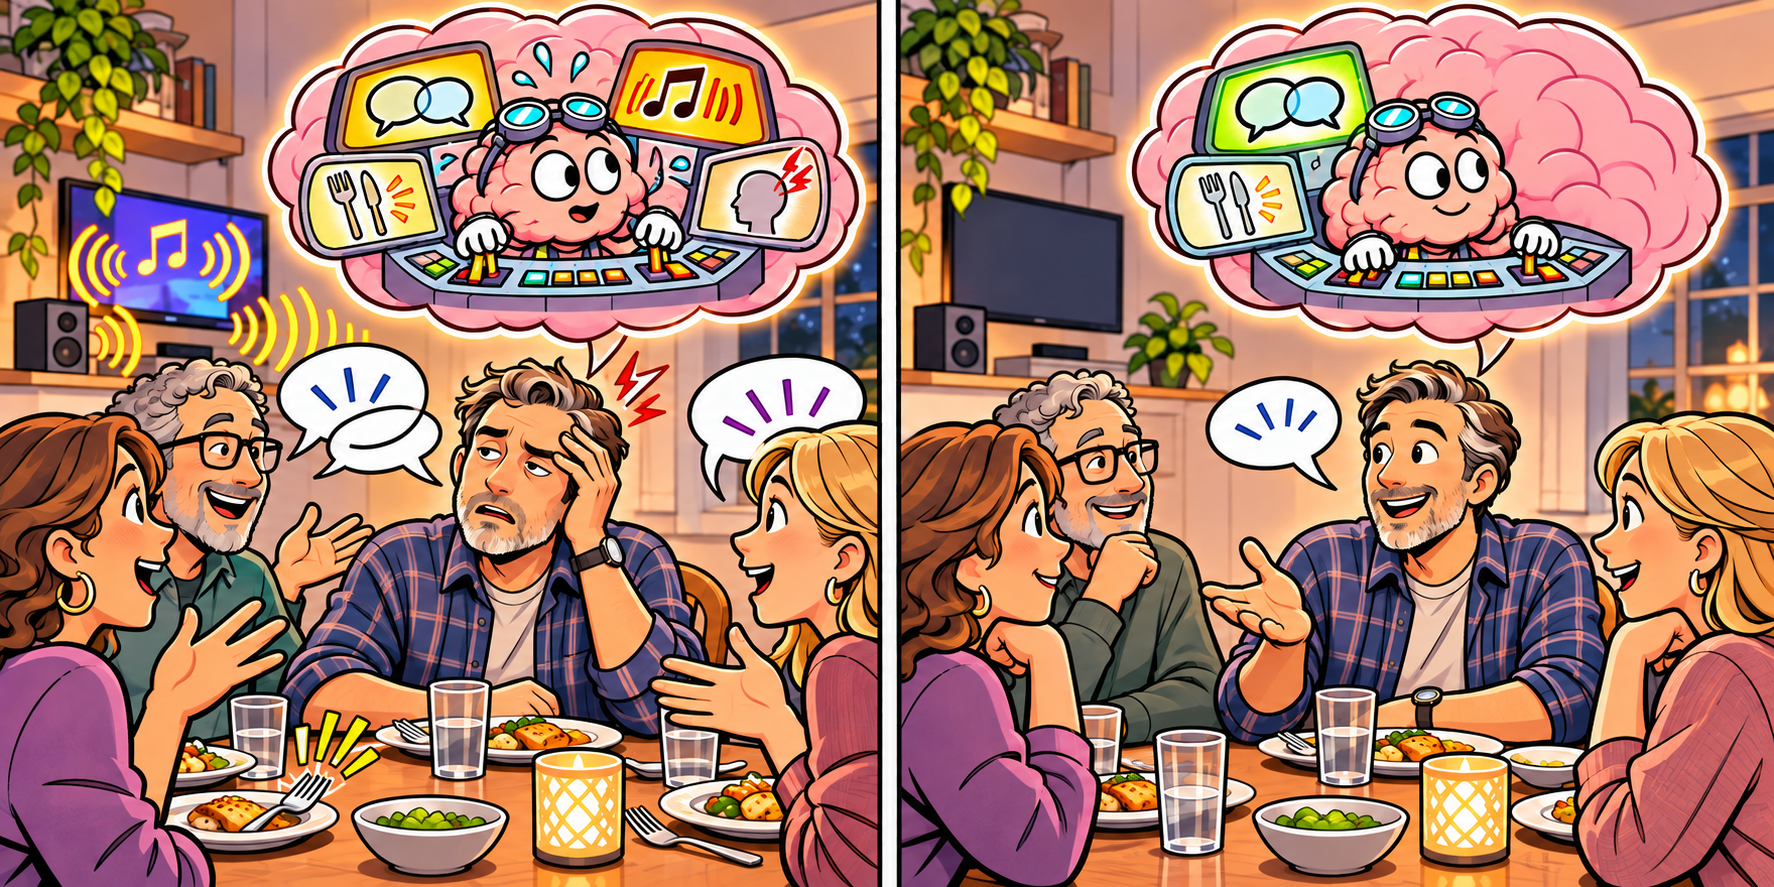
Feedback loops can help us, too
Not every feedback loop makes life harder.
Imagine returning home from the café.
You sit somewhere comfortable and quieter.
Now it’s easier to follow what someone is saying.
You don’t need to work as hard to hear them.
With less effort, you may have more energy available for the conversation.
That improvement might make the activity easier still.
Here’s another example.
You’re learning a new skill.
You make a small improvement, which gives you confidence to practise again.
That practice helps you improve further.
The important point is that feedback loops can work in helpful directions as well as difficult ones.
And sometimes, changing just one part of a situation changes what happens next.
What might this have to do with FND?
Now we can connect these ideas to our nervous system research.
In Lesson 18, we learned that the brain prepares for what it expects.
In Lesson 19, we learned about the different kinds of information it receives.
Today we’ve learned that some information receives greater attention and that the nervous system’s readiness can change.
Scientists are interested in how these abilities work together in FND.
Think about someone who has functional movement difficulties.
Their brain needs information about the movement, their body’s position and what they’re trying to accomplish.
Attention and readiness can influence how they carry out a task.
Some functional symptoms vary when the person’s attention shifts or when the demands of the activity change.
Scientists are studying whether differences in networks that help select important information, prepare actions and respond to bodily signals contribute to some of these experiences.
They are also interested in whether changes in symptoms can affect attention and readiness, which may then influence the person’s experience of the next activity.
These possible interactions give researchers specific questions to investigate. Their relevance can differ between symptoms and people. [2]
The idea is useful because it helps us ask a different question.
Instead of only asking, “What started this symptom?” we can also ask:
What might be making this situation harder right now?
Sometimes those are two very different questions.
What if the symptoms themselves become important?
Imagine you’re trying to read a message.
You notice that your hand has begun trembling.
The movement catches your attention.
Now you’re finding it harder to concentrate on the message because you’re noticing your hand.
The difficulty reading may make the task more frustrating.
And that extra demand may make it harder to continue.
Does this prove that attention caused the tremor?
No.
But it shows how a symptom can become another important piece of information competing for attention.
The same idea may be relevant when dizziness, pain, unusual sensations or cognitive difficulties interrupt an activity.
A symptom can change what you notice, how much effort the task requires and how ready you feel to respond.
This is one reason the effects of FND can extend beyond the symptom itself.
When sensory overload changes your day
Consider someone whose nervous system becomes overwhelmed by sounds, lights or several demands happening together.
They might describe a busy supermarket as exhausting, even when the shopping itself is straightforward.
One person in the FND community described getting help from an occupational therapist:
“My OT helped me … learn exercises to calm myself and avoid sensory overwhelm.”
Figure 1. Community experience — finding practical help with sensory demands. [7]
Their experience shows what practical help meant to them; useful support will look different for different people.
Notice what makes the example interesting.
The therapist wasn’t necessarily changing the person’s hearing or eyesight.
They were helping the person find ways to manage the demands of sensory information in everyday life.
The word calm in the quotation also doesn’t mean the person was necessarily anxious. Reducing sensory demands and changing the body’s level of readiness can be useful for reasons other than emotion.
That distinction will matter when we explore emotions later in this module.
Can these ideas help with assessment and recovery?
Yes. And we’ve already encountered some of the reasons.
A clinician might ask whether your symptoms change in a crowded environment, during a demanding activity or when several things compete for attention.
They may also observe how movement or communication changes under different conditions, when it’s safe and clinically appropriate.
Those observations can contribute to understanding your symptoms and planning care.
For rehabilitation, a therapist might help you change part of an activity.
An occupational therapist could help make an environment more manageable.
A physiotherapist might help you practise a movement using an appropriate task or cue.
A speech-language therapist might consider whether communication becomes easier when unnecessary demands are reduced.
These are examples of individualized care, not a set of exercises everyone should follow. [4][5][6]
Sometimes the most useful change is surprisingly ordinary: a quieter place to talk, a shorter task, a clearer instruction or a different way to participate.
The aim isn’t always to remove every difficult sensation.
It’s to find conditions that help you do something meaningful, safely and with less unnecessary effort.
What about emotions?
You may have noticed that we haven’t spent much time discussing anger, sadness, fear or other emotions.
That’s deliberate.
Salience and arousal are important whether you’re feeling emotional or not.
Pain can demand attention. Physical activity can increase arousal. A loud sound can interrupt concentration.
Before we explore emotions, we’ll look at how thinking and memory can become difficult—even during ordinary activities. That will help us understand why emotional conversations can become harder, too.
For now, we’ve learned something different.
Our nervous system doesn’t simply receive information. It decides what deserves priority, adjusts its readiness and responds to changes that may affect one another.
What have we learned?
Salience helps explain why some information stands out.
Arousal describes how alert and ready your nervous system is to respond.
Feedback loops describe how changes can continue affecting one another, sometimes making an experience harder and sometimes helping it improve.
These ideas may help us understand why the demands of an activity matter, especially when living with FND and other health conditions.
They also give us useful questions to explore with our care team.
Something to think about
Imagine trying to talk with a friend in a busy café. There’s music, people moving around, and perhaps pain or tiredness competing for your attention. Which demands would be hardest for you to set aside? Does something similar happen during another ordinary activity?
How might that feel?
When several demands pile up, what part of the activity do you most want to keep enjoying? Perhaps it’s the conversation, being out with someone, or simply having enough energy to stay a little longer.
One small step
See whether one demand could be made smaller without losing the part you enjoy. A quieter seat, the television turned off during a conversation, or fewer instructions at once may be enough. If a change to your surroundings already helps, it may also be useful in another activity. There’s no need to provoke symptoms to find out.
Next, we’ll explore cognitive difficulties: why questions, words and familiar information sometimes seem to disappear, and how this relates to—but isn’t the same as—a diagnosis of FCD.
Optional crossword
Revisit the lesson with a crossword. The easy edition includes a word bank.
Optional colouring activity

Open the Lesson 20 colouring PDF (new tab), or browse the colouring collection.
For the Person With FND
For Family, Friends, and Other Supporters
For Clinicians and the Care Team
Research and Sources
For Family, Friends, and Other Supporters
When a pleasant evening becomes difficult
You’ve invited a couple of friends over for dinner.
Your partner has FND and has been looking forward to seeing them.
Everyone is enjoying themselves. There’s food on the table, a little music playing and plenty to talk about.
Then the conversation becomes livelier.
Two people begin talking at once. Someone laughs loudly. Plates and cutlery clatter as dinner is cleared away.
Your partner becomes quieter.
When someone asks a question, they take longer to answer.
A few minutes later, they lose track of what they were saying.
You notice the change.
“Are you getting tired?” you ask.
“A bit. There’s just so much going on.”
You look around. It’s a perfectly ordinary dinner with friends.
And yet something that was enjoyable half an hour ago has become difficult.
What changed?
The sounds haven’t changed for everyone
Think about sitting in a restaurant.
You might barely notice the music, the conversations around you or the sound of dishes being collected. Your attention is on the person across the table.
Our nervous systems are constantly deciding which information deserves attention. Scientists call this salience.
Something meaningful, unexpected or uncomfortable can become particularly important to the brain.
Your name being spoken across a crowded room might catch your attention. So might a sudden noise or a painful sensation.
Now imagine that several things keep demanding your attention.
You’re trying to listen to someone, but the music seems impossible to ignore. Your chair is uncomfortable. You’re also dealing with a headache, and every time someone speaks loudly, you lose part of the conversation.
You might still enjoy being there.
But following the discussion has become a lot more work.
For someone living with FND, migraine, sound sensitivity or cognitive difficulties, these competing demands can make an otherwise ordinary gathering particularly difficult.
What looks like a comfortable social setting to one person may require considerable effort from another.
What does this have to do with FND?
Researchers are investigating whether differences in brain networks involved in salience, attention and arousal contribute to certain functional neurological symptoms. These networks help the nervous system identify important information and prepare responses. Their possible involvement in FND forms part of broader scientific models of the condition. [1][2]
Arousal is another useful word here. It describes how alert and ready the nervous system is to respond.
It’s easy to associate arousal with anxiety, but it also changes during excitement, physical activity, pain and illness.
Your partner might be having a wonderful evening while their nervous system is working hard to manage everything happening around them.
That distinction can change how we interpret what we see.
Someone becoming quiet, having difficulty speaking or needing to leave a gathering might appear upset or uninterested.
But the difficulty may have much more to do with the demands of the situation than with how they feel about the people around them.
And sometimes, the person themselves won’t know why an activity has suddenly become harder.
When one difficulty adds to another
Let’s return to dinner.
Your partner is trying to answer a question, but several conversations are happening nearby.
They concentrate harder to follow what’s being said.
That extra effort becomes tiring.
As they become more tired, following the next question becomes harder still.
Now they’re working even harder just to stay in the conversation.
One difficulty is adding to another.
Scientists call this kind of interaction a feedback loop: when one change influences another, which then affects what happens next.
You may have experienced something similar yourself. Perhaps a poor night’s sleep made concentrating difficult, and the extra effort left you even more exhausted.
The important thing to understand is that the person may be using more effort while appearing to do less.
Someone who becomes quieter isn’t necessarily withdrawing from the conversation. They may be struggling to remain part of it.
And when a functional symptom itself becomes difficult to ignore, it can add another demand to everything else the person is managing.
That doesn’t tell us what originally caused the symptom. It helps us understand why continuing the activity might now be harder.
Sometimes changing one thing helps
Suppose your partner mentions that the noise is becoming uncomfortable.
You could ask whether they’d like the music turned off.
Perhaps they would.
With one less sound competing for attention, they might find it easier to follow the conversation.
Or perhaps they’d prefer moving somewhere quieter for a while.
Someone else might use earplugs or noise-cancelling devices in certain situations. But those aren’t always comfortable. Some people find that earplugs make chewing or their own voice sound unpleasantly loud.
A quieter room might therefore work better than asking them to keep their earplugs in throughout dinner.
There’s something nice about this kind of adjustment.
You haven’t had to understand exactly what’s happening in their brain. You’ve simply learned a little more about what the evening feels like to them.
And perhaps the change benefits everyone. Guests can still enjoy their conversation, while your partner finds it easier to join in.
What if the difficulty continues?
Even after the music stops, your partner may remain tired or find conversation difficult.
They might decide they’ve enjoyed enough company for one evening.
Or they may want to stay and listen without having to answer every question.
Both can be ways of remaining connected to something they enjoy.
It’s also possible that neither of you noticed how demanding the evening had become until the symptoms were already difficult.
That happens.
You don’t need to work out every contributing factor or anticipate every problem.
Over time, you may both discover which arrangements make certain activities more enjoyable. A quieter dinner might help. Another time, the person may prefer a shorter visit or a different setting.
And sometimes the plans won’t need changing at all.
What can supporters take from this lesson?
Salience helps explain why some information becomes difficult to ignore. Arousal concerns how ready the nervous system is to respond. Feedback loops help us understand how one difficulty may add to another.
For supporters, these ideas are useful because they reveal something we don’t always see.
A person may be enjoying an activity while finding it increasingly difficult to participate. They may be concentrating harder even as their answers become shorter, their movements more difficult or their energy less available.
Understanding that can make an ordinary question feel more thoughtful:
“Would it be easier if we turned the music off?”
It leaves room for the person to explain what they need—or to say they’re quite happy as things are.
Sometimes the kindest change isn’t asking someone to try harder to keep up. It’s making the activity a little easier to enjoy together.
For the Person With FND
For Family, Friends, and Other Supporters
For Clinicians and the Care Team
Research and Sources
For Clinicians and the Care Team
Why some information takes priority
Lesson 19 explored the different sources of sensory information available to the nervous system. Yet receiving information is only part of the picture. The brain must also determine what deserves priority and adjust its readiness to respond.
Three concepts help explain these interactions.
Salience describes the importance or relevance assigned to information, influencing what attracts processing priority. A familiar voice, a meaningful goal or a painful sensation may all be highly salient. Importance does not necessarily imply danger.
Arousal describes physiological and cognitive readiness to respond. It changes with activity, excitement, pain, sleep, illness and other demands. Although anxiety may influence arousal, the two are not synonymous.
A feedback loop occurs when changes in one factor influence another, which in turn affects the first. Such interactions can increase difficulty, help maintain a stable state or support improvement.
These distinctions become useful when clinicians observe that a person’s functional abilities change as several demands compete for the nervous system’s resources.
Clinical case: When communicating becomes harder
Samira is a fictional patient with an established diagnosis of functional speech symptoms following appropriate specialist assessment.
She attends a follow-up appointment to discuss her treatment and ask several questions.
Samira can usually communicate her needs during a quiet conversation. Today, two clinicians are present, questions come quickly, and computer notifications repeatedly interrupt the discussion.
She also has persistent pain and has slept poorly.
As the appointment progresses, her speech becomes increasingly hesitant. She loses the opportunity to finish several answers and eventually reaches for the notes she brought with her.
One clinician notices that Samira spoke more comfortably at the beginning of the appointment.
What might explain the change?
Understanding what is competing for priority
Several features of the appointment may be clinically relevant.
Samira is trying to formulate answers while listening to multiple people speak. The questions matter because they concern her treatment. Background sounds and interruptions repeatedly compete with the conversation.
Each demand may attract attention for a different reason.
The questions are meaningful. The notifications are unexpected. Her pain may also be difficult to ignore.
This is where salience becomes useful: it helps explain why information can attract processing priority even when the person would prefer to concentrate elsewhere.
Samira’s difficulty also occurs in the context of poor sleep, pain and sustained effort. These factors can influence alertness and physiological readiness, making arousal relevant to the formulation.
But nothing in the observation establishes that Samira is anxious. Nor can the clinician infer her autonomic state or a particular neural mechanism from the visible change in speech.
The important clinical observation is more straightforward: communication became more difficult as the demands of the appointment increased.
That offers an opportunity to understand which demands are relevant to Samira and how the interaction might become more accessible.
Where might a feedback loop develop?
Consider what happened as Samira began struggling to answer.
She may have needed more effort to organize and produce her speech. That effort could contribute to fatigue, making subsequent questions more difficult. As answers became harder, other people may have repeated questions or spoken for her, inadvertently adding further demands.
A possible interaction emerges:
Greater communication difficulty leads to increased effort. Increased effort contributes to fatigue. Fatigue makes further communication more demanding.
This illustrates a potential feedback loop affecting participation.
It does not demonstrate that fatigue caused Samira’s functional speech symptoms, that a specific neural loop has been identified, or that she could interrupt her symptoms through conscious effort.
The relationship could also work in other directions. Speech difficulty itself may increase effort and fatigue, while pain, poor sleep or other factors may influence several parts of the interaction simultaneously.
Recognizing these possibilities helps clinicians avoid mistaking the sequence of events for proof of causation.
It also reveals something practical: even when the cause of a symptom remains uncertain, the demands surrounding it may still be modifiable.
What could make the appointment more accessible?
Samira came to the appointment to explain her concerns and participate in treatment decisions. That goal remains important whether her speech becomes easier or not.
A quieter conversation, one speaker at a time and sufficient opportunity to finish an answer might reduce the competing demands. Her written notes could provide an additional way to communicate what matters to her.
These possibilities address the organization of the interaction rather than assuming that Samira must first regulate her nervous system.
Why might that help?
A more manageable communication environment may reduce the effort involved in following questions, selecting a response and making herself understood. It also makes room for the communication strategies Samira already finds useful.
Speech-language therapy consensus recommendations support individualized communication assessment and treatment, including attention to task and conversational context. Occupational therapy consensus similarly recognizes the importance of environmental demands, activity adaptation and participation. [4][5]
These principles provide a rehabilitation rationale for considering Samira’s experience within the activity itself.
They do not establish that reducing background noise will normalize salience-network activity or reverse a particular FND mechanism.
What would meaningful improvement look like?
Suppose the appointment continues with fewer interruptions and Samira uses her notes when speaking becomes difficult.
Her speech might become easier, but it might also remain impaired.
In either situation, the interaction could become more successful.
Did Samira explain her concerns? Could she ask the questions she prepared? Was she able to participate in decisions without another person unnecessarily speaking for her? Did the changes reduce effort or discomfort?
These are meaningful functional outcomes.
They also offer information for future care. If a particular communication arrangement consistently improves access, it may remain valuable even when the neurological symptom persists.
Conversely, if communication remains difficult, that provides a reason to consider whether a different approach, more specialized assessment or additional support could help.
An accommodation can be clinically successful because it improves participation, without demonstrating that the underlying symptom has been treated.
What does the research contribute?
Seeley and colleagues (2007) identified distinguishable intrinsic connectivity networks associated with salience-related processing and executive control in a general neuroscience study. [1]
This work supports the importance of studying how the brain identifies relevant information and coordinates different processing demands.
Drane and colleagues (2021) subsequently described an FND framework involving interactions among attention, salience, arousal and other neural and psychological processes. [2]
Why do these findings matter? They provide a scientific basis for investigating relationships among information priority, physiological readiness and functional symptoms. They also help explain why clinicians might consider several interacting demands rather than searching for a single environmental trigger.
However, the general network findings do not establish what happened in Samira’s brain during the appointment. The FND framework describes proposed mechanisms rather than a validated individual causal test.
The useful clinical application is therefore to examine the demands affecting a meaningful activity and consider whether changing one of them improves participation.
A reported improvement would support the practical value of the adjustment, not prove the proposed neural explanation.
When other clinical perspectives become relevant
Samira’s experience may be adequately addressed through adjustments to the appointment and communication strategies she already uses.
If her functional speech difficulties continue to interfere with everyday communication, speech-language therapy may offer more specialized assessment and rehabilitation. Occupational therapy may contribute when broader sensory or environmental demands repeatedly limit participation.
Pain, sleep disruption, medication effects and other health conditions may also influence Samira’s available capacity and deserve appropriate clinical consideration.
Psychological support may be valuable when Samira identifies distress, adjustment difficulties or other relevant concerns. Its role can be explained through those needs rather than assuming that visible arousal or functional speech symptoms establish an emotional cause.
The same distinction matters with other FND presentations. Functional seizures, for example, require their own diagnostic and safety considerations, including evaluation of coexisting epilepsy and clinically significant changes. [3]
New palpitations, presyncope, breathing difficulties or other systemic complaints cannot be explained simply by labeling them arousal. Appropriate medical assessment remains relevant to the actual presentation.
Professional collaboration is most useful when it addresses a particular unanswered question or functional need.
What should clinicians take from this lesson?
Salience, arousal and feedback describe different aspects of nervous-system function.
Salience concerns what receives priority. Arousal concerns readiness to respond. Feedback describes how changes may influence one another over time.
These concepts can enrich an individualized clinical formulation, particularly when symptoms and participation vary with activity demands, pain, fatigue or environmental conditions.
In Samira’s case, they help explain why the appointment itself deserves attention. The clinical opportunity is to understand how communication becomes difficult, consider what could make the interaction more accessible and evaluate whether the result supports her participation.
The scientific models remain useful without needing to establish a specific neural cause for that change.
Clinical takeaway: Consider how competing demands, readiness and possible feedback interactions affect functional participation. Their value lies in generating better clinical questions and identifying meaningful adaptations, while assessment and outcomes remain grounded in the individual rather than an assumed neural mechanism.
For the Person With FND
For Family, Friends, and Other Supporters
For Clinicians and the Care Team
Research and Sources
Further reading in the Reference Library
For practical detail, see sensory profiles and the environment and emotional regulation and overwhelm.
Research and Sources
General salience-network research and an FND framework inform the explanation. Clinical guidance supports individualized assessment and rehabilitation; the community quotation illustrates one person’s experience of occupational therapy.
| Citation | Figure | Full citation |
|---|---|---|
| [1] | — | Seeley WW, Menon V, Schatzberg AF, et al. Dissociable intrinsic connectivity networks for salience processing and executive control. J Neurosci. 2007;27:2349–2356. doi:10.1523/JNEUROSCI.5587-06.2007. Original · PubMed. FND-CIT-0304. |
| [2] | — | Drane DL, Fani N, Hallett M, Khalsa SS, Perez DL, Roberts NA. A framework for understanding the pathophysiology of functional neurological disorder. CNS Spectr. 2021;26:555–561. doi:10.1017/S1092852920001789. Original · PubMed. FND-CIT-0006. |
| [3] | — | Tolchin B, Goldstein LH, Reuber M, et al. Management of functional seizures practice guideline executive summary: report of the AAN Guidelines Subcommittee. Neurology. 2026;106:e214466; online December 10, 2025. doi:10.1212/WNL.0000000000214466. Original · PubMed. FND-CIT-0010. |
| [4] | — | Baker J, Barnett C, Cavalli L, et al. Management of functional communication, swallowing, cough and related disorders: consensus recommendations for speech and language therapy. JNNP. 2021;92:1112–1125. doi:10.1136/jnnp-2021-326767. Original · PubMed. FND-CIT-0025. |
| [5] | — | Nicholson C, Edwards MJ, Carson AJ, et al. Occupational therapy consensus recommendations for functional neurological disorder. JNNP. 2020;91:1037–1045. doi:10.1136/jnnp-2019-322281. Original · PubMed. FND-CIT-0011. |
| [6] | — | Bennett K, Diamond C, Hoeritzauer I, et al. A practical review of functional neurological disorder (FND) for the general physician. Clin Med. 2021;21:28–36. doi:10.7861/clinmed.2020-0987. Original · PubMed. FND-CIT-0001. |
| [7] | Figure 1 | Public Reddit contribution, r/FND. Original. Account of occupational-therapy help with sensory demands. Excerpt and surrounding context checked November 3, 2026. Individual experience; the excerpt does not establish a treatment effect or validate the theory mentioned in the full comment. FND-CIT-0324. |